












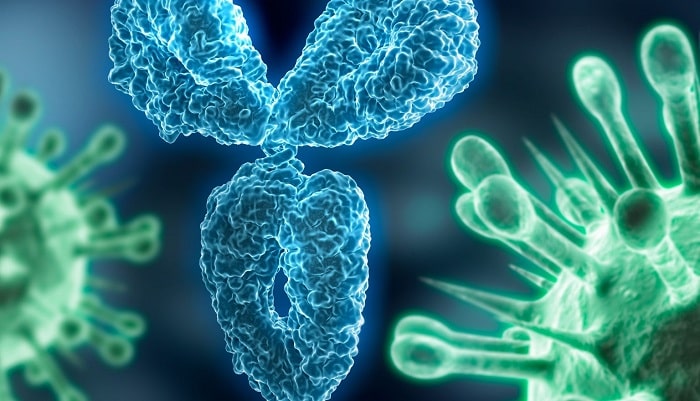
Beyond cancer, there are a number of sectors that provide considerable prospects for antibody drug conjugates (ADCs), using their capacity to deliver therapeutic drugs selectively to sick cells or tissues while avoiding off-target effects. These opportunities may be used in a number of different fields. Several preclinical and clinical studies are now being conducted to investigate the potential of ADCs in various domains, which are currently in the process of being developed.
All of the following are the primary areas in which ADCs are displaying potential:
Infectious illnesses include:
Infections Caused by Bacteria Alternative drug delivery systems (ADCs) have the ability to target particular bacterial pathogens and administer medicines directly to the bacteria. This has the potential to minimize antibiotic resistance and preserve beneficial microbiota.
For the treatment of viral illnesses such as HIV and hepatitis, antiviral drugs (ADCs) may be created to target viral proteins, which presents a novel approach to the treatment of viral diseases.
Diseases caused by allergies:
In the case of rheumatoid arthritis, anti-inflammatory drugs (ADCs) that target certain immune cells or inflammatory mediators have the potential to provide more targeted therapy choices with fewer possible adverse effects. Systemic lupus erythematosus (SLE): Targeting particular immunological pathways using anti-drug conjugates (ADCs) may help lower disease activity and improve patient outcomes.
Neurological conditions include:
Alzheimer’s disease: ADCs that target amyloid-beta plaques or tau protein aggregates may provide novel therapy options for neurodegenerative illnesses by targeting these specific protein aggregates. ADCs have the potential to be used in the treatment of multiple sclerosis by performing selective targeting and modulation of pathogenic immune cells or inflammatory processes in the central nervous system.
Heart and blood vessel diseases:
Atherosclerosis: Alternative drug delivery systems (ADCs) might be designed to target and deliver medications to atherosclerotic plaques, which could possibly stabilize the plaques and avoid cardiovascular events.
Heart Failure: Using ADCs to target particular pathways involved in cardiac remodelling and fibrosis might potentially allow for the development of novel therapeutic approaches for the treatment of heart failure.
Complications of metabolism:
ADCs have the potential to target and modify insulin resistance or inflammation of diabetes, both of which are related with the condition.
Obesity: Adipose tissue or particular metabolic pathways might be targeted by ADCs, which could lead to the development of novel therapies for obesity and other metabolic illnesses associated with obesity.
Disorders of the haematologic system:
The usage of ADCs might be used to transport clotting factors or other therapeutic agents directly to the site of bleeding in patients with hemophilia, therefore enhancing the effectiveness of the treatment and minimizing the adverse effects.
Anaemia: The enhancement of therapy for different types of anaemia might be achieved with the targeted delivery of erythropoiesis-stimulating drugs to the bone marrow through the use of ADCs.
The illnesses of fibrosis:
Idiopathic pulmonary fibrosis is one of the disorders that might potentially be treated using ADCs because of their ability to target and control fibrotic pathways in the lungs.
Fibrosis of the Liver: Targeted treatments that make use of ADCs have the potential to bring about a reduction in liver fibrosis and to stop the development of cirrhosis.
Which investment in research and development to prioritize?
A number of factors, including market need, scientific feasibility, regulatory environment, competitive landscape, potential for breakthrough cures, strategic fit, alliances, and financial considerations, have been taken into account in order to arrive at this prioritization.
Because of the high prevalence of cancer and the huge amount of unfulfilled demands in this field, oncology gets a big amount of investment budget. Additionally, oncology provides the potential to treat serious disorders that pose a danger to one’s life, in addition to offering significant returns. However, other therapeutic areas, including autoimmune illnesses, infectious diseases, and neurological disorders, can draw substantial investment if they exhibit major unmet needs, a huge number of people who are directly impacted, and a dearth of therapies that are successful.
The availability of targets that have been well characterized is of the utmost importance, and oncology is receiving the advantages of considerable research that has identified tumor-specific antigens, which makes it an ideal environment for the creation of ADCs. The research of non-oncological indications is made possible by advancements in ADC technology, such as enhanced linkers and more effective cytotoxic payloads. These advancements drive investment choices based on the scientific viability of these domains.
As a result of the important nature of the illnesses, oncology often has faster approval procedures, which attracts investment in research and development. Accelerated programs, such as the FDA’s Breakthrough Therapy Designation and Fast Track, have the potential to minimize risk and shorten the amount of time needed for product development. In addition, the establishment of regulatory mechanisms that are both clear and helpful for non-oncological illnesses might promote investment in such areas.
There is a lot of rivalry in the area of cancer, which may cause businesses to look for possibilities in industries that are less congested. These businesses will evaluate the number of rivals and the state of competing medicines. Therapeutic domains that have a smaller number of rivals or innovative targets might be appealing to businesses because they provide them with the opportunity to build leadership and distinguish their particular goods.
Investment in oncology is driven by the realization that there is a chance of finding medicines that considerably enhance either survival rates or quality of life. Similarly, if the therapeutic promise is significant, the possibility to produce revolutionary medicines in other areas, such as autoimmune or genetic illnesses, might attract investment. This is because of the promising nature of the possible treatments.
Companies often concentrate their efforts on domains that are congruent with their core strengths and the knowledge they already possess. One firm that has a strong concentration on oncology may give ADCs in cancer a higher priority than other companies, while other companies that have competence in other sectors may invest in those areas. Another method is portfolio diversification, in which businesses invest in a variety of therapeutic areas in order to minimize risk and maximize opportunity throughout the investment process.
The priorities of research and development might be influenced by partnerships and collaborations. Through collaboration with research organizations, biotech businesses, and academic institutions, one may get access to new targets, technology, and knowledge, which in turn drives investment in certain areas.
After that, businesses analyze the possible return on investment (ROI), taking into account the expenses of development, the amount of time it takes to bring the product to market, price, and reimbursement chances. It is common for oncology treatments to fetch high pricing, which may result in a larger return on investment. It is more probable that projects that have identified financial streams and resources that are readily available would be given priority.
Due to the complicated composition of ADCs, which includes a monoclonal antibody, a cytotoxic agent, and a linker, the process of developing and producing ADCs is a tough endeavor. In order to bring these medicines to market in a manner that is both safe and successful, it is necessary to overcome technological, scientific, and regulatory obstacles. This needs knowledge from several disciplines and rigorous systems.
Key hurdles include selecting and optimizing the components, such as discovering antibodies that target particular cells with high specificity, selecting effective cytotoxic medicines with low harm to healthy cells, and designing stable linkers that release the drug within target cells. These are only some of the obstacles that need to be overcome. The attainment of exact and uniform conjugation, the guarantee of batch consistency, and the preservation of molecular integrity are all essential components for satisfying regulatory approval.
In order to manufacture ADCs, it is necessary to increase production while preserving quality, to navigate complicated procedures, and to execute stringent quality control systems. It is vital to address stability difficulties and try to optimize storage conditions in order to guarantee effectiveness and safety over an extended period of time.
It is necessary to minimize off-target effects and strike a balance between the therapeutic window in order to guarantee both safety and effectiveness. When it comes to effectively bringing ADC medicines to market, it is vital to successfully navigate complicated regulatory procedures, provide thorough data, manage high research costs, and get favorable reimbursement.
Part contract development manufacturing organizations (CDMOs) play
CDMOs are quite important. This ensures that pharmaceutical businesses are able to overcome technical, logistical, and regulatory obstacles, resulting in efficient development, high-quality standards, and timely market launch. They offer pharmaceutical companies with the experience and infrastructure necessary to overcome these obstacles.
The ability to produce antibodies, linker technology, and cytotoxic drug conjugation are all examples of the specialized expertise that CDMOs bring to the table. They provide highly developed skills for the creation of processes, including the optimization of conjugation procedures and purification techniques. The creation of high-quality ADCs that have constant drug-to-antibody ratios (DAR), purity, stability, and potency is ensured by the use of cutting-edge manufacturing facilities and extensive analytical services.
The provision of regulatory assistance is yet another essential service that CDMOs provide. This service assists ADCs in navigating the complex regulatory environment and ensures that they are in conformity with worldwide standards. The support that they provide in compiling paperwork and data for submissions to regulatory agencies is really beneficial. By outsourcing to contract manufacturing organizations (CMOs), pharmaceutical businesses are able to concentrate on their core strengths while also using the experience of the CDMO to maximize the use of resources and speed up the development timetable.
There are a lot of CDMOs that provide end-to-end services, which include everything from early-stage research to commercial-scale production and packaging. This helps to ensure continuity and reduce the risks associated with knowledge transfer. They do this by investing in cutting-edge technology and engaging in techniques of continuous improvement, which ultimately results in an increase in the quality and efficiency of ADC manufacturing. The development of the ADC may be better coordinated with the assistance of dedicated project management, which also helps to ensure that goals and schedules are reached.
It is possible for pharmaceutical firms to share the risks that are connected with the development and production of ADCs if they form partnerships with CDMOs. For the purpose of assuring continuity in the supply chain and limiting risks linked to process failures, regulatory impediments, and market uncertainty, CDMOs often have contingency plans in place. These plans are designed to tackle unanticipated problems.
The successful licensure of ADC therapeutics is contingent upon the availability of comprehensive preclinical evidence, which includes the validation of targets, the mechanism of action, and a stringent safety profile. For a treatment to be considered clinically effective, it must exhibit substantial advantages, such as increased survival, via well conducted clinical trials that meet the required patient criteria and objectives.
When it comes to safety and tolerability, it is essential to have an efficient treatment of adverse events and a therapeutic window that is favorable. The perfection of manufacturing guarantees the creation of ADCs of a constant and high-quality, with production that can be scaled from clinical to commercial levels.
The beginning of contact with regulatory bodies and the creation of full dossiers that include preclinical, clinical, and manufacturing data are both components of regulatory strategy. The creation of biomarkers and companion diagnostics are very important for the identification of patients and the provision of individualized therapy.
The protection of market share may be achieved via the use of legislative incentives and a robust intellectual property portfolio. Market access, reimbursement, price, and a dependable distribution network are all required components of a commercial strategy in order to ensure broad availability.
As part of the post-approval obligations, Phase IV studies and comprehensive pharmacovigilance programs are being implemented to assess the long-term safety and effectiveness of the drug. Taking these precautions guarantees that ADC treatments will continue to be successful and safe.
The next-generation linkers and payloads for greater stability and selectivity are examples of innovations in ADC technology. Additionally, bispecific and multi-specific ADCs that target several antigens for enhanced effectiveness are other examples of these types of modifications.
The expanding therapeutic applications that are on the horizon include more study into illnesses that are not related to oncology as well as personalized medicine techniques that make use of biomarkers for developing customized medicines. Further enhancement in effectiveness is anticipated to be achieved by the use of combination therapies and dual-function ADCs, which incorporate additional treatments or gene-editing techniques.
Continuous production and automation are two examples of manufacturing technologies that will boost scalability and cost-efficiency to a greater extent. The clearance process may become more streamlined if worldwide harmonization of standards is implemented, and regulatory frameworks are expected to become more adaptable in the future. Furthermore, increased investments, strategic collaborations, and solid intellectual property protections will drive future development and market expansion. At the same time, sustainable pricing and favorable reimbursement rules seek to guarantee that patients have access to affordable healthcare and that it is affordable to them.


