













Close

Innovations In Biologic Drug Delivery Beyond Injections

Note* - All images used are for editorial and illustrative purposes only and may not originate from the original news provider or associated company.

Related stories

Managing Quality and Regulatory Risks in Pharmaceutical Technology Transfer

Technology transfer moves more than manufacturing instructions. It moves process knowledge, supplier dependencies, labeling requirements, packaging specifications, and the evidence needed to demonstrate control. For medical device manufacturers, including those supporting drug-device combination products, these interfaces can become recurring sources of compliance gaps during site transitions, acquisitions, and remediation. The central problem is often not a missing procedure. It is a quality system that allows connected activities to change independently. A label revision may be approved while packaging artwork, supplier instructions, or production-system data still reflect an obsolete version. Staying inspection-ready requires manufacturers to manage these dependencies as one controlled system. Why Compliance Gaps Keep Recurring Findings are treated as documentation defects Revising a procedure can resolve an immediate discrepancy without changing the behavior that caused it. If unclear decision rights, weak escalation, or ineffective training remain, the same failure may surface elsewhere. Corrective and preventive action should distinguish the observed finding from its underlying cause and establish how effectiveness will be demonstrated. Ownership is divided across connected functions Quality, Regulatory Affairs, labeling, packaging engineering, operations, suppliers, and digital-system owners often maintain separate workflows. Each team may complete its assigned task while an interface remains uncontrolled. For example, changing an instruction for use can affect packaging configuration, translations, technical documentation, inventory disposition, and release controls. Transitions expose unresolved weaknesses Acquisitions and site transfers can introduce conflicting procedures, incomplete knowledge transfer, or different assumptions about validated processes. Regulatory changes add further demands. When these events coincide with CAPA or change-control backlogs, teams may prioritize administrative closure over risk reduction. Without a coordinated impact assessment, local fixes can create new gaps downstream. Establish the Regulatory Baseline Inspection readiness starts with knowing which requirements apply to the product, activity, and market. Pharmaceutical, device, and combination-product obligations are not interchangeable; transfer planning should identify the applicable requirements rather than assume one quality framework covers every operation. According to FDA’s Quality Management System Regulation overview and FAQs, the QMSR became effective on February 2, 2026, incorporates ISO 13485:2016 by reference, and introduced the updated device inspection process under Compliance Program 7382.850. ISO 13485 certification does not exempt a manufacturer from FDA inspection or guarantee compliance with FDA requirements. For devices marketed in the European Union, Regulation (EU) 2017/745, Annex I, Section 23, provides the primary requirements for information supplied with devices, including labels and instructions for use. Teams should assess the applicable provisions alongside relevant language, product-specific, and market requirements. A labeling review should therefore evaluate required content and consistency with the device’s intended purpose and supporting documentation—not merely artwork accuracy. How to Identify the Real Gaps Begin with a cross-functional assessment that follows actual product and information flows. Select representative transfers, label changes, supplier changes, and CAPAs, then trace each from initiation through implementation and effectiveness review. Map dependencies: Identify affected specifications, suppliers, packaging components, systems, validation activities, and training. Compare records with practice: Check whether approved procedures match what operators and reviewers actually do. Test traceability: Follow a requirement through technical documentation, labeling, production instructions, and release evidence. Examine recurrence: Look for repeated deviations, reopened actions, overdue changes, and findings shared across sites. Assess capacity: Determine whether qualified owners have enough time and authority to complete corrective work. Prioritize gaps by potential patient or user harm, regulatory impact, likelihood of recurrence, and detectability. Document the rationale; an old overdue item is not automatically more important than a newly identified high-risk weakness. Align Quality, Labeling, Packaging, and Change Control Create a coordinated remediation plan with one accountable owner for each action, named contributors, acceptance criteria, and required evidence. Separate immediate containment from systemic correction. Containment might prevent obsolete labels from being issued; correction might redesign approval and implementation controls so obsolete versions cannot return. Use change control as the integration point. Before approval, evaluate effects on regulatory submissions or notifications, technical documentation, supplier controls, packaging performance, validation, electronic master data, inventory, and training. Record both identified impacts and justified decisions that particular activities are unaffected. During technology transfer, define readiness gates before production or release responsibilities move. These should address the transfer of process knowledge, acceptance criteria, receiving-site capability, required qualification or validation, approved documents, and personnel competence. The appropriate evidence depends on the product and process; a generic checklist cannot replace a documented assessment. Finally, verify implementation where the work happens. Confirm that current instructions are available, suppliers received approved requirements, systems contain correct versions, and affected personnel can perform their tasks. A signed approval is not evidence that every downstream change took effect. Mistakes That Undermine Inspection Readiness Closing CAPAs on task completion alone: Effectiveness checks should test whether the underlying failure has been controlled. Updating labels in isolation: Assess packaging, supplier, system, documentation, and inventory consequences. Counting closures instead of evidence: Dashboards need defensible records behind their status indicators. ...

State of API & Peptide CDMO Capacity

Pharmaceutical companies planning peptide or complex small-molecule launches are...

Identifying Sex Specific Outcomes Through Real-World Data Analysis

The pharmaceutical sector is increasingly turning to large-scale datasets...
- Advertisement -

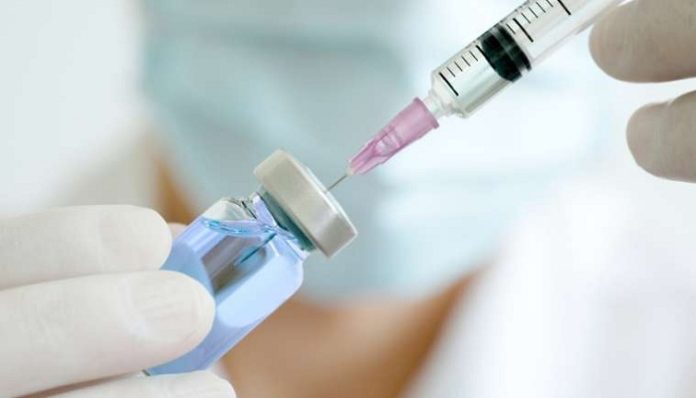
Despite their track record of demonstrating significant therapeutic efficacy, biologics still face daunting challenges in their drug delivery. Biologics such as monoclonal antibodies (mAbs) and some vaccines are largely administered via injection or by infusion. These methods can often be a barrier to patient compliance. Less invasive forms of biologic drug delivery are in development, particularly oral administration and inhalation routes.

The current rapid rate of new drug target discoveries, coupled with increasingly effective engineering processes and a growing knowledge and understanding of how biologics are processed in the body have resulted in a higher number of biologics in clinical development and approved for the market. However, to date, formulations of biologics have mostly been designed for the parenteral route of administration. Because of this design, many biologics have short plasma half-lives which require frequent administration. The need to use needles on a frequent basis leads to sometimes painful administration and ultimately poor patient compliance.

Addressing the challenges

Frank Tagliaferri, PhD, chief scientific officer at Pace Life Sciences, emphasizes that biologics are typically larger molecules with more structural requirements as opposed to small-molecule therapeutics. The latter has long dominated the traditional oral route of delivery. Biologics also encounter more structural sensitivities that need to be overcome, Tagliaferri says.

These limitations often result in poor bioavailability for a variety of reasons, including degradation while in the alimentary tract, inability to overcome intestinal cell or mucosal barriers, and first-pass metabolism, which is avoided with the traditional injection routes, Tagliaferri explains. He further adds that, While there may be beneficial solutions to these hurdles individually, it is a significant challenge to overcome all of them with what will generally be a higher-cost biologic drug where extremely low bioavailability is not always economically feasible.

Today, alternative biologics drug delivery methods that have shown promise include inhaled biologics and oral solid biologics. Past-case scenarios include inhaled insulins. As Tagliaferri notes, the utility of inhaled biologics showed some promise during the development of both the Pfizer and Mankind inhaled insulin products, where numerous technical hurdles for lung delivery were overcome. But the lack of a commercial success to date demonstrates that issues such as ergonomics, patient-to-patient variability, and high cost of goods all contribute to public acceptance and the ultimate success of an alternate route.

Oral solid biologics, on the other hand, possess different, but just as significant, challenges compared to inhaled biologics, Tagliaferri says. Yet, there appears to have been more significant progress in oral solid biologics, he avers. The small-molecule development history has provided several delivery enhancements to oral delivery that have been successfully applied to a limited number of biologics. These include techniques such as enteric coating of capsules, additives to control release and residence time in the gut, [and] physical formulation techniques such as spray drying or lyophilization designed to help stabilize the molecules, Tagliaferri explains. When we combine these techniques with advancements in the use of additives to protect molecules or enhance delivery such as polymers, penetration enhancers, chelating agents, etc., there has been success as demonstrated in the delivery of some metabolic enzymes to the gut using spray dried proteins and enterically coated capsules.

Tagliaferri also observes that there does not seem to be a universal needle-fee path for all biologics. Rather, depending on the molecule, dose, and intended site of action, current alternative options such as inhaled, nasal, transdermal, buccal, oral, etc., would all have some utility in the market. Due to its convenience, compliance, and overall acceptance, however, the oral route will continue to be aggressively pursued and—with emphasis on future particle engineering or novel excipient advancements—may eventually be achieved, he says.

Where are we now?

At a 2022 Oxford Global conference on formulation and delivery, speakers discussed how the field of inhaled biologics had reached an interesting phase of development. Speakers noted how scientists are currently working on optimizing the process by focusing on methods that reduce the necessary dose needed to be effective and delivering the biologic to the site of action. They point to one example in which researchers are working toward more specific delivery to target organs in the body, such as cancer cells in the lungs, rather than the conventional treatment which targets the whole body via injection. However, developing an inhaled biologics formulation for this case scenario, and others, requires overcoming the issues inherent with creating stable and safe formulations for biologics.

Much work is currently going into developing biologics formulations that can be inhaled to deliver therapy locally to the lungs for treating respiratory diseases, according to speakers at the 2022 conference. The work has led to innovations that include antisense oligonucleotides, messenger RNA (mRNA), and lipid nanoparticles (LNPs), the speakers noted. The speakers also noted that the recent interest in developing inhaled and nasal biologics was partly spurred by the urgency seen during the development of COVID-19 vaccines and treatments for other viral pathogens.

Meanwhile, more progress was made on oral vaccines with the completion in 2023 of a Phase I clinical trial for an oral vaccine platform known as QYNDR, which is a self-administered drinkable vaccine, reportedly the first of its kind, according to US Specialty Formulations, a manufacturer of sterile injectable, topical, and specialty pharmaceuticals.

QYNDR, a next-generation protein-based oral vaccine (mucosal vaccine), was developed as a means to address challenges seen with current COVID-19 vaccines. In the results from the Phase I clinical trial, the vaccine demonstrated longevity and cross-variant protection from multiple COVID-19 strains. The study may have also possibly identified a correlation of protection against the virus and other strains, which the company will be further investigating in a Phase II clinical trial.

The Phase I clinical data showed strong evidence that this oral platform and vaccine is a revolutionary industry disruptor and will become the preferred method of vaccination in the future, said Kyle Flanigan, CEO of USSF, in a press release issued at the time that the Phase I trial was completed. As they proceed into Phase II and III, we are confident this next-generation vaccine will be more effective than other mucosal vaccines in current development and testing.


Never miss a pharmaceutical headline

The pharmaceutical industry moves fast – stay on top of it with our must - read briefings.

  • The top pharma and life sciences stories, straight to your inbox
  • The biggest news, features, interviews, and analysis
  • Dedicated coverage of the key developments driving the global pharmaceutical sector

Subscribe

- Never miss a story with notifications

- Gain full access to our premium content

- Browse free from any location or device.

Media Packs

Expand Your Reach With Our Customized Solutions Empowering Your Campaigns To Maximize Your Reach & Drive Real Results!

– Access the Media Pack Now

– Book a Conference Call

– Leave Message for Us to Get Back

Latest stories

Related stories

Managing Quality and Regulatory Risks in Pharmaceutical Technology Transfer

Technology transfer moves more than manufacturing instructions. It moves process knowledge, supplier dependencies, labeling requirements, packaging specifications, and the evidence needed to demonstrate control. For medical device manufacturers, including those supporting drug-device combination products, these interfaces can become recurring sources of compliance gaps during site transitions, acquisitions, and remediation. The central problem is often not a missing procedure. It is a quality system that allows connected activities to change independently. A label revision may be approved while packaging artwork, supplier instructions, or production-system data still reflect an obsolete version. Staying inspection-ready requires manufacturers to manage these dependencies as one controlled system. Why Compliance Gaps Keep Recurring Findings are treated as documentation defects Revising a procedure can resolve an immediate discrepancy without changing the behavior that caused it. If unclear decision rights, weak escalation, or ineffective training remain, the same failure may surface elsewhere. Corrective and preventive action should distinguish the observed finding from its underlying cause and establish how effectiveness will be demonstrated. Ownership is divided across connected functions Quality, Regulatory Affairs, labeling, packaging engineering, operations, suppliers, and digital-system owners often maintain separate workflows. Each team may complete its assigned task while an interface remains uncontrolled. For example, changing an instruction for use can affect packaging configuration, translations, technical documentation, inventory disposition, and release controls. Transitions expose unresolved weaknesses Acquisitions and site transfers can introduce conflicting procedures, incomplete knowledge transfer, or different assumptions about validated processes. Regulatory changes add further demands. When these events coincide with CAPA or change-control backlogs, teams may prioritize administrative closure over risk reduction. Without a coordinated impact assessment, local fixes can create new gaps downstream. Establish the Regulatory Baseline Inspection readiness starts with knowing which requirements apply to the product, activity, and market. Pharmaceutical, device, and combination-product obligations are not interchangeable; transfer planning should identify the applicable requirements rather than assume one quality framework covers every operation. According to FDA’s Quality Management System Regulation overview and FAQs, the QMSR became effective on February 2, 2026, incorporates ISO 13485:2016 by reference, and introduced the updated device inspection process under Compliance Program 7382.850. ISO 13485 certification does not exempt a manufacturer from FDA inspection or guarantee compliance with FDA requirements. For devices marketed in the European Union, Regulation (EU) 2017/745, Annex I, Section 23, provides the primary requirements for information supplied with devices, including labels and instructions for use. Teams should assess the applicable provisions alongside relevant language, product-specific, and market requirements. A labeling review should therefore evaluate required content and consistency with the device’s intended purpose and supporting documentation—not merely artwork accuracy. How to Identify the Real Gaps Begin with a cross-functional assessment that follows actual product and information flows. Select representative transfers, label changes, supplier changes, and CAPAs, then trace each from initiation through implementation and effectiveness review. Map dependencies: Identify affected specifications, suppliers, packaging components, systems, validation activities, and training. Compare records with practice: Check whether approved procedures match what operators and reviewers actually do. Test traceability: Follow a requirement through technical documentation, labeling, production instructions, and release evidence. Examine recurrence: Look for repeated deviations, reopened actions, overdue changes, and findings shared across sites. Assess capacity: Determine whether qualified owners have enough time and authority to complete corrective work. Prioritize gaps by potential patient or user harm, regulatory impact, likelihood of recurrence, and detectability. Document the rationale; an old overdue item is not automatically more important than a newly identified high-risk weakness. Align Quality, Labeling, Packaging, and Change Control Create a coordinated remediation plan with one accountable owner for each action, named contributors, acceptance criteria, and required evidence. Separate immediate containment from systemic correction. Containment might prevent obsolete labels from being issued; correction might redesign approval and implementation controls so obsolete versions cannot return. Use change control as the integration point. Before approval, evaluate effects on regulatory submissions or notifications, technical documentation, supplier controls, packaging performance, validation, electronic master data, inventory, and training. Record both identified impacts and justified decisions that particular activities are unaffected. During technology transfer, define readiness gates before production or release responsibilities move. These should address the transfer of process knowledge, acceptance criteria, receiving-site capability, required qualification or validation, approved documents, and personnel competence. The appropriate evidence depends on the product and process; a generic checklist cannot replace a documented assessment. Finally, verify implementation where the work happens. Confirm that current instructions are available, suppliers received approved requirements, systems contain correct versions, and affected personnel can perform their tasks. A signed approval is not evidence that every downstream change took effect. Mistakes That Undermine Inspection Readiness Closing CAPAs on task completion alone: Effectiveness checks should test whether the underlying failure has been controlled. Updating labels in isolation: Assess packaging, supplier, system, documentation, and inventory consequences. Counting closures instead of evidence: Dashboards need defensible records behind their status indicators. ...

State of API & Peptide CDMO Capacity

Pharmaceutical companies planning peptide or complex small-molecule launches are...

Identifying Sex Specific Outcomes Through Real-World Data Analysis

The pharmaceutical sector is increasingly turning to large-scale datasets...

Strengthening Clinical Evidence Through Female Cohort Representation

The pharmaceutical industry is undergoing a fundamental shift in...

Subscribe

- Never miss a story with notifications

- Gain full access to our premium content

- Browse free from any location or device.

Media Packs

Expand Your Reach With Our Customized Solutions Empowering Your Campaigns To Maximize Your Reach & Drive Real Results!

– Access theMedia Pack Now

– Book a Conference Call

– Leave Message for Us to Get Back

Translate »